ALS genetics
for the neurology registrar
Evan Edmond
Neurology ST8
structure
- Scenarios
- What to do in the clinic
- Is ALS genetic?
- C9orf72
- SOD1
- FUS
Scenarios
A 57 year old man presents with progressive painless wasting and weakness in all 4 limbs with upper and lower motor neuron signs. His father had a dementia onset aged 60 with a marked change in behaviour and a preference for sweet foods.
The two children of a patient with ALS without a wider family history accompany their parent (mother) to clinic. After routine discussion about the causes of ALS, the patient expresses a wish to have all known genetic causes excluded. One of the children becomes angry, saying not to do this as he does not want to find out that he is at an increased risk of getting the disease.
A 16-week pregnant woman with ALS without a family history requests rapid genetic testing to guide termination if an ALS gene variant is found.
A 30-year-old patient with ALS but without a family history requests genetic testing and is found to have a C9ORF72 hexanucleotide repeat expansion. At a subsequent appointment, the patient is accompanied by both parents, who are asymptomatic.
A patient with ALS without a family history and with a lower motor neurone-predominant phenotype arranges private whole-genome sequencing, which reports a variant of uncertain significance in ABCD1. The patient is concerned that they have been misdiagnosed.
A patient with ALS without a family history and with a typical progression rate has read about gene-targeting trials in SOD1-mediated ALS. They request genetic testing so that they might be eligible to enrol. It reveals that they are heterozygous for a ‘likely pathogenic’ variant associated with a characteristically very slowly progressive, typically homozygous recessive form of ALS.
structure
- Scenarios
- What to do in the clinic
- Is ALS genetic?
- C9orf72
- SOD1
- FUS
Phenotype
- ALS remains largely a clinical diagnosis
- Spectrum - pure motor, pure cog, both
- Age of onset
- Rate of progression
- caution re: genetics as a shortcut to diagnosis
Family history
Not just ALS
- Lost weight, mobility/speech declined rapidly at end of life?
- Dementia - AD misdiagnosed?
- Alcohol abuse, bipolar, schizophrenia?
- Chestnuts - adoption, non-paternity, consanguinity
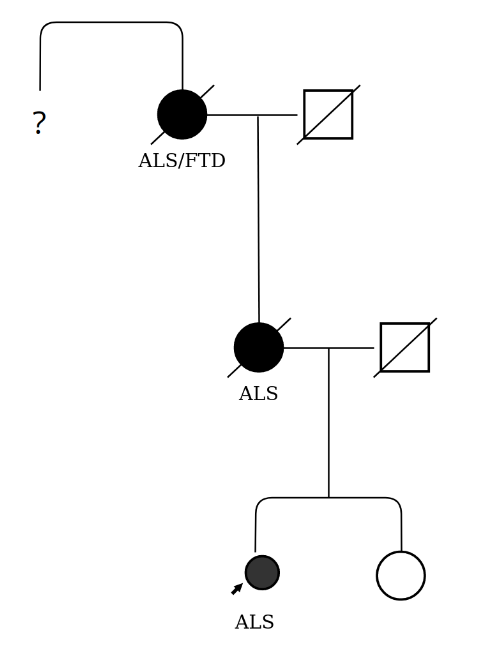
When to discuss genetics?
- Patient wants to know
- Research/clinical trial access
- Patient doesn't want to know
- Patient hasn't thought about it
- Family dynamics - beware the anxious healthy biological relative who has read up
structure
- Scenarios
- What to do in the clinic
- Is ALS genetic?
- C9orf72
- SOD1
- FUS
Is ALS genetic?
- What have we learned from familial ALS?
- How heritable is sporadic ALS?
- Do we need a new model?
How common is familial ALS?
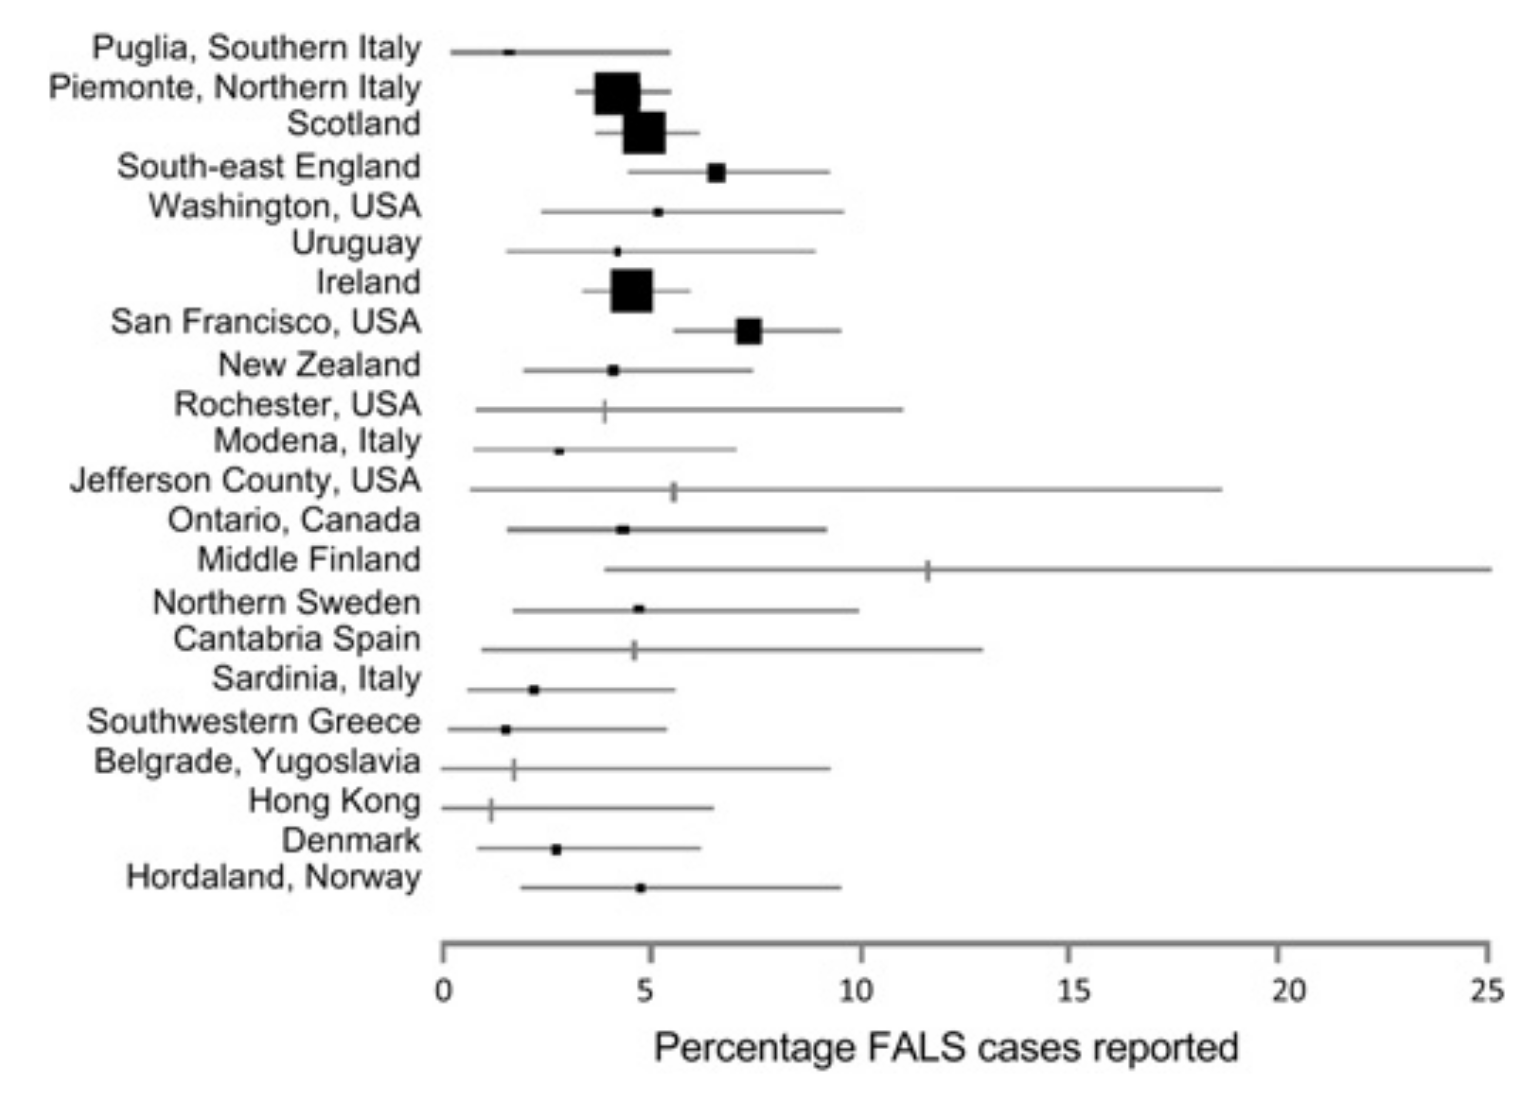
Byrne et. al. JNNP 2011.
doi
- Uncommon - 5-10%
- Geographically variable
- guesswork with family history
- clinical ALS only
- variable definition of familial
Limitations of older studies
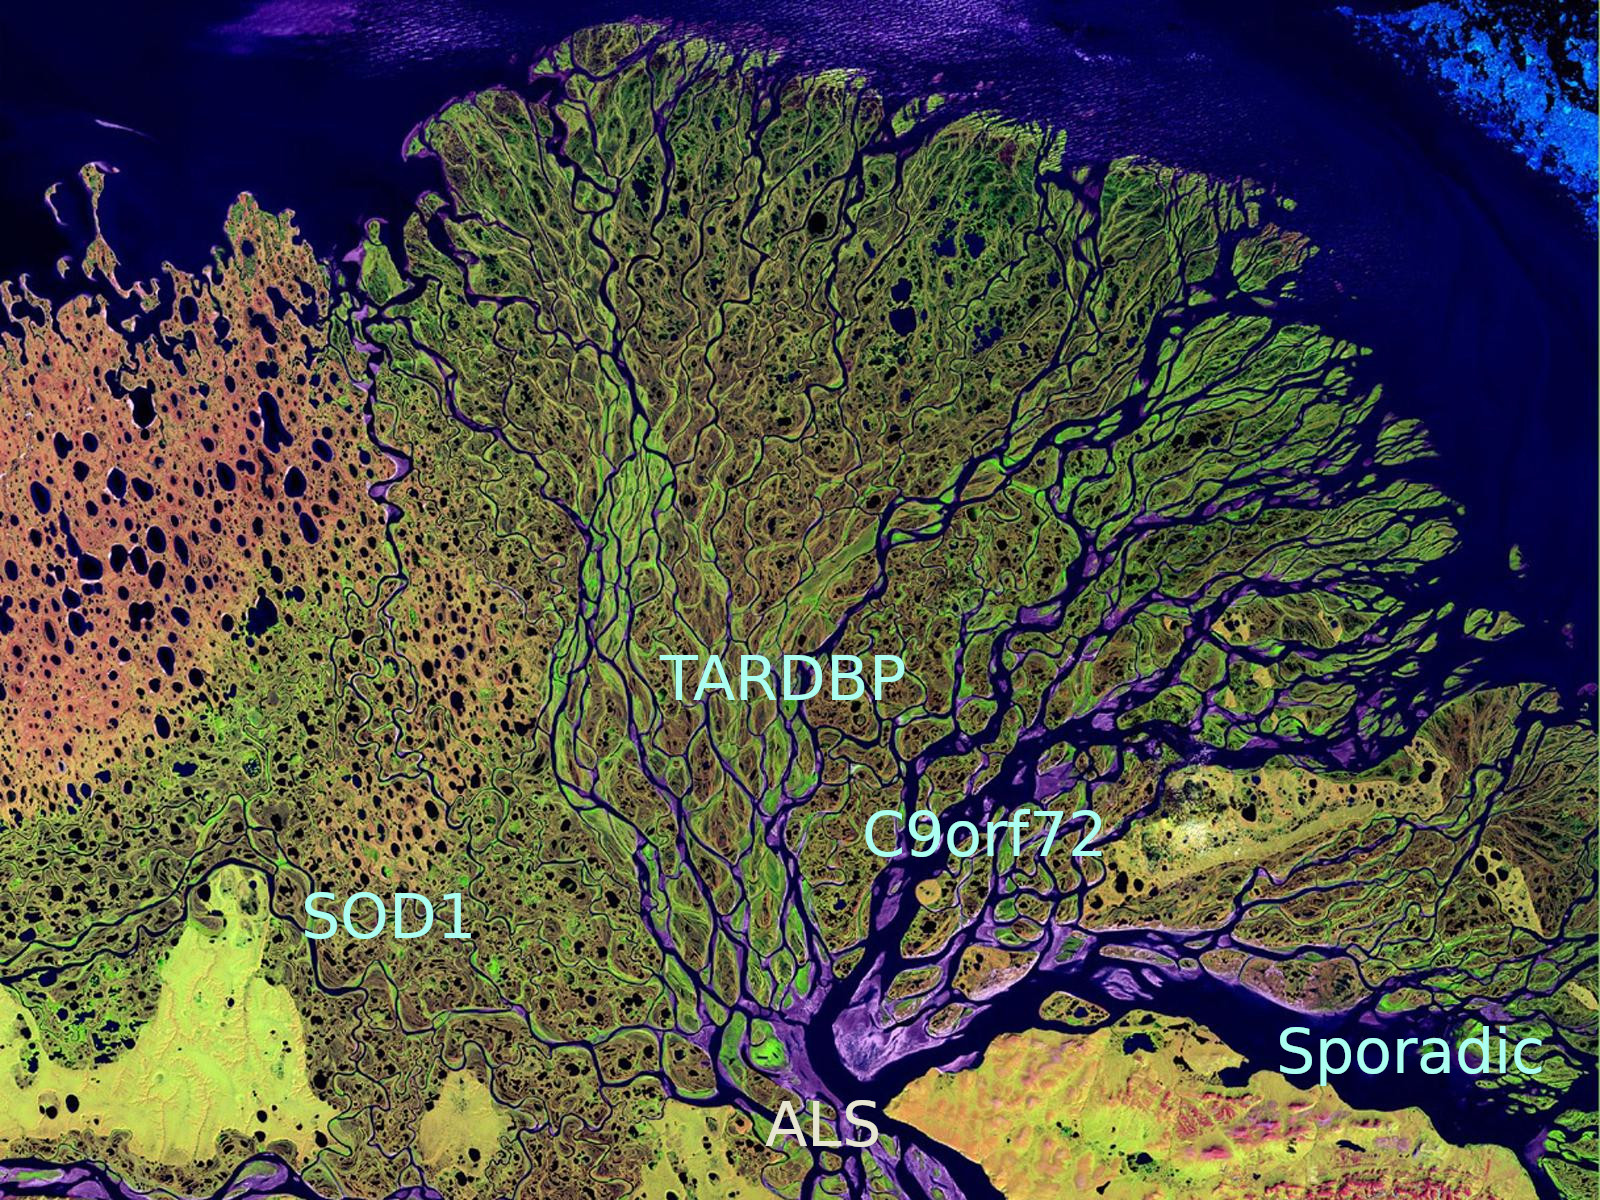
Linkage studies in familial ALS have identified several key genes

SOD1

TDP-43

C9orf72

FUS
How heritable is sporadic ALS?
Family pairs in Irish register
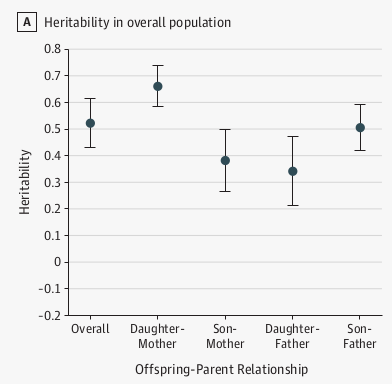 Ryan et. al. 2019 JAMA N doi
Germline monogenic causes only explain ~15% of apparently sporadic ALS
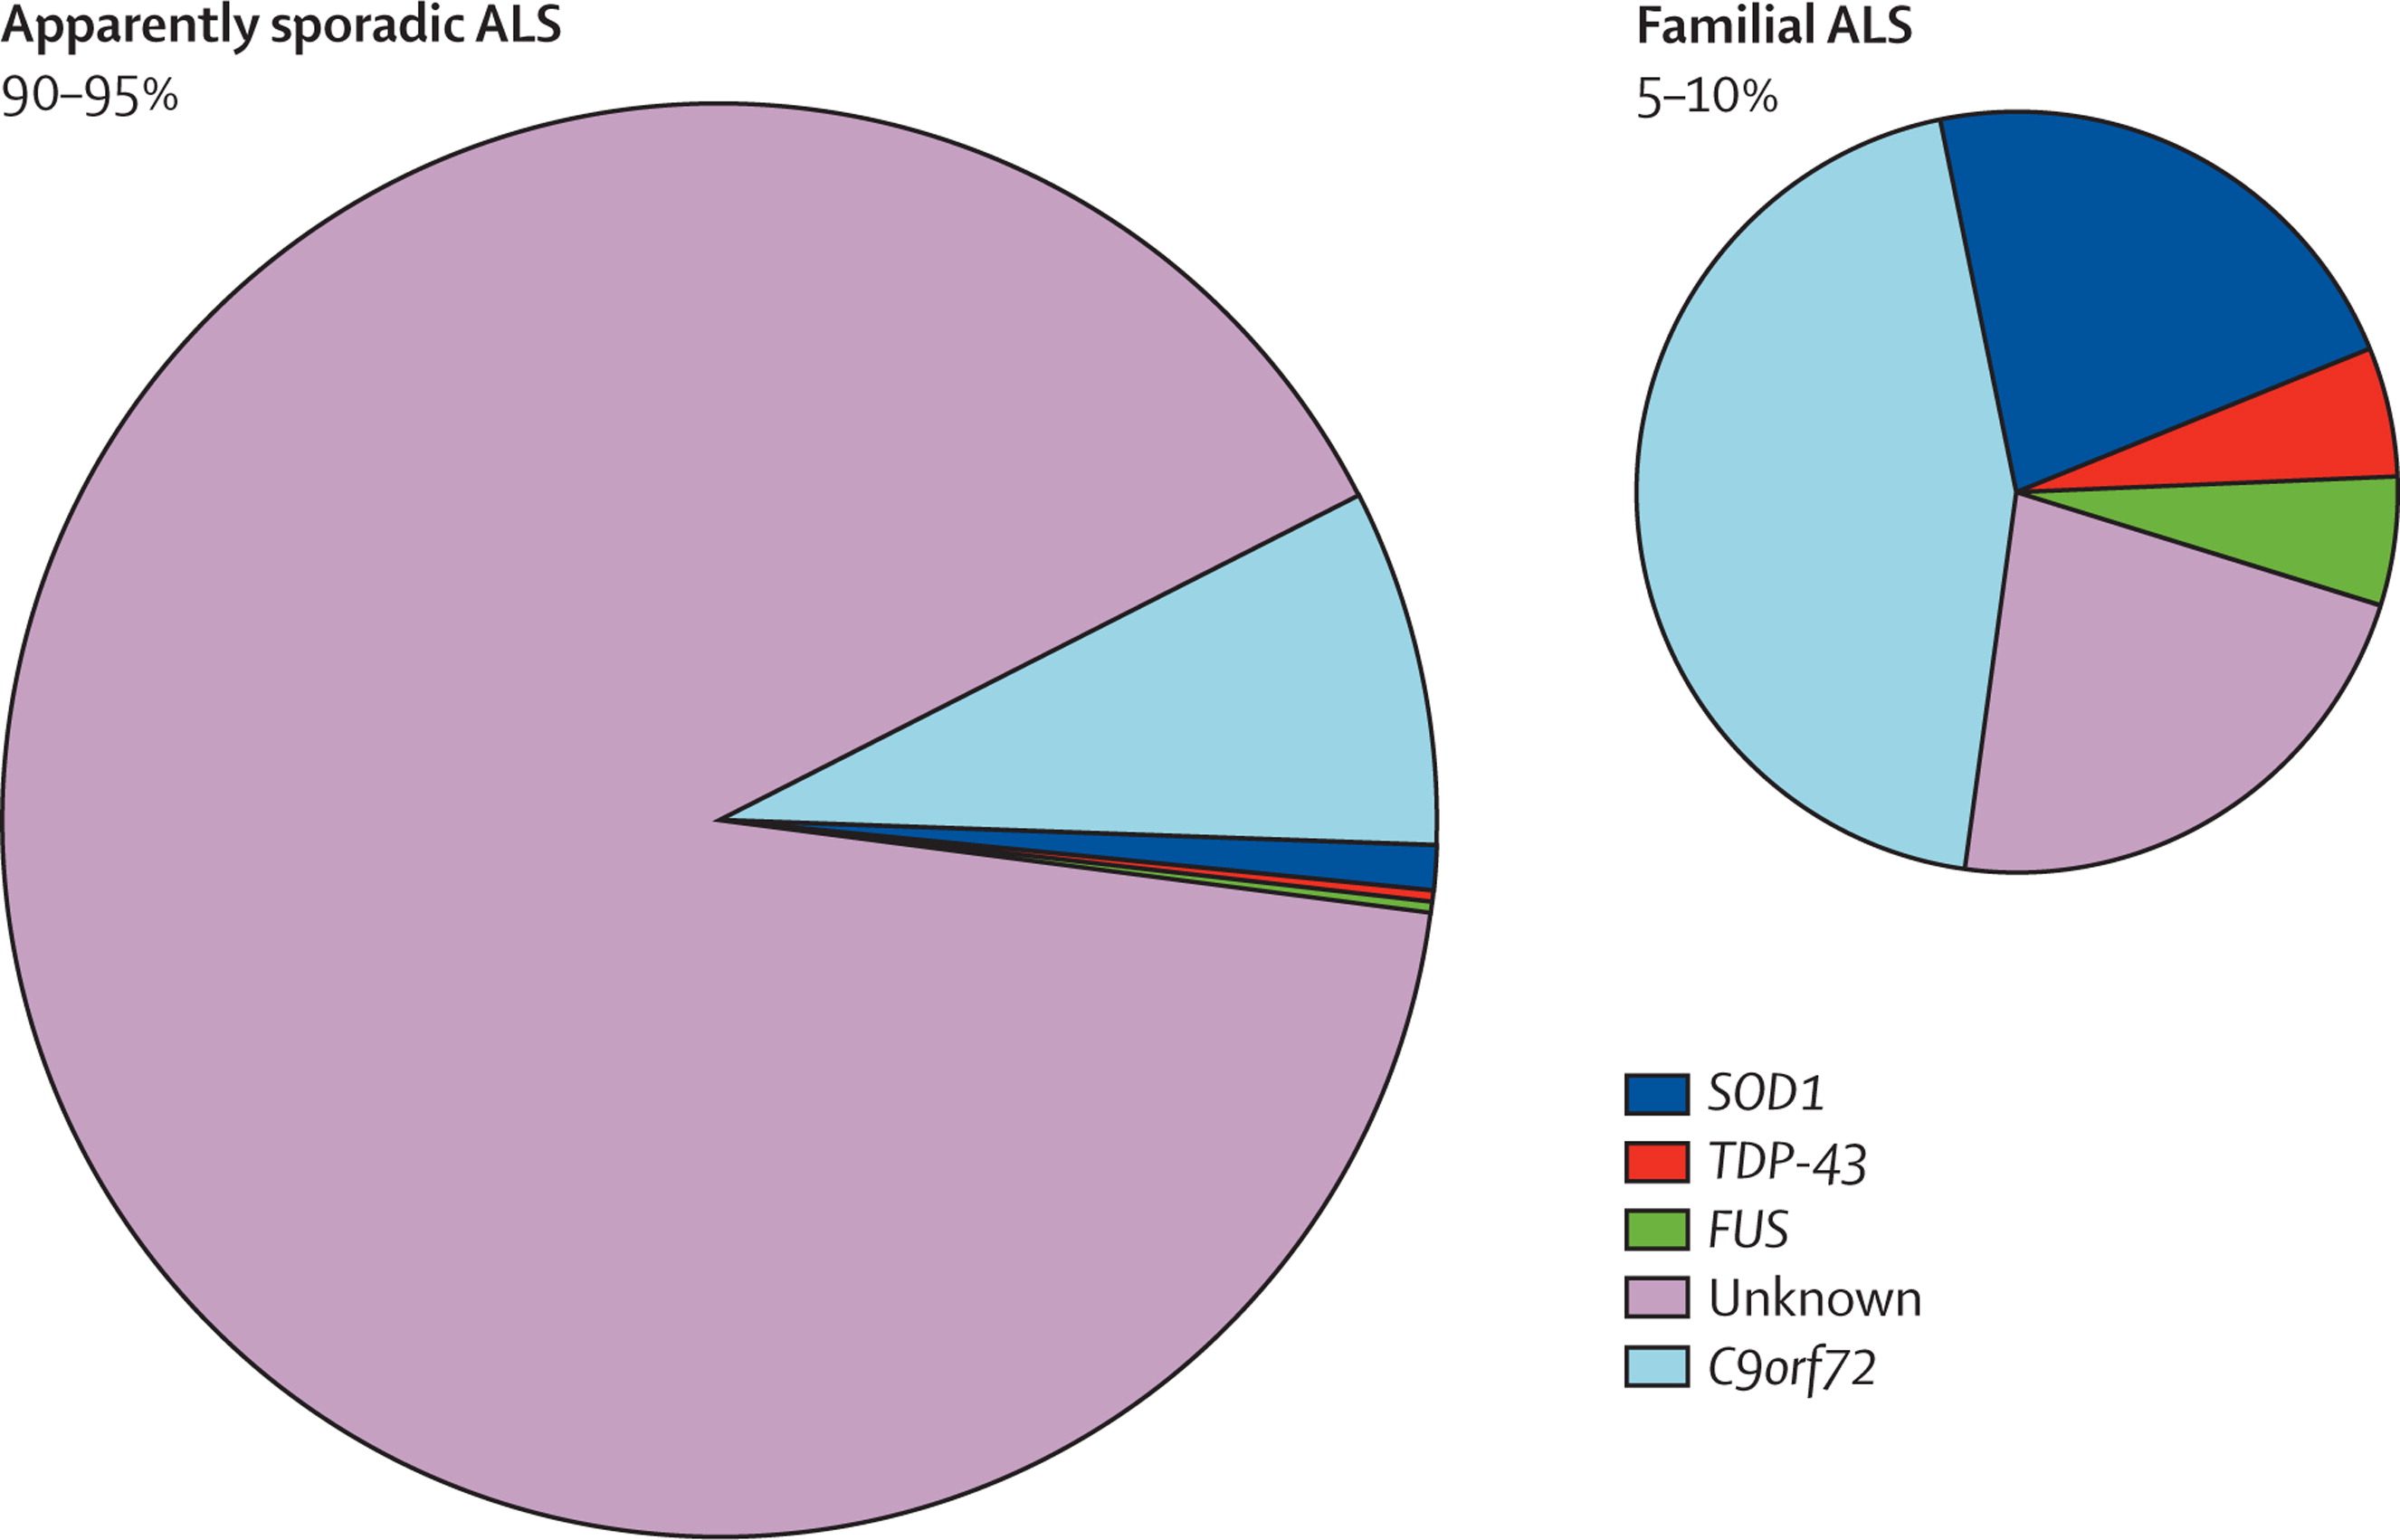
'Missing' heritability
Do we need a new model?
- Mutations are not equivalent
- Currently unknown non-genetic modifiers of penetrance and severity
Testing - ALS patients
- DNA storage
- Targeted genes
- Panel
- WGS virtual panel
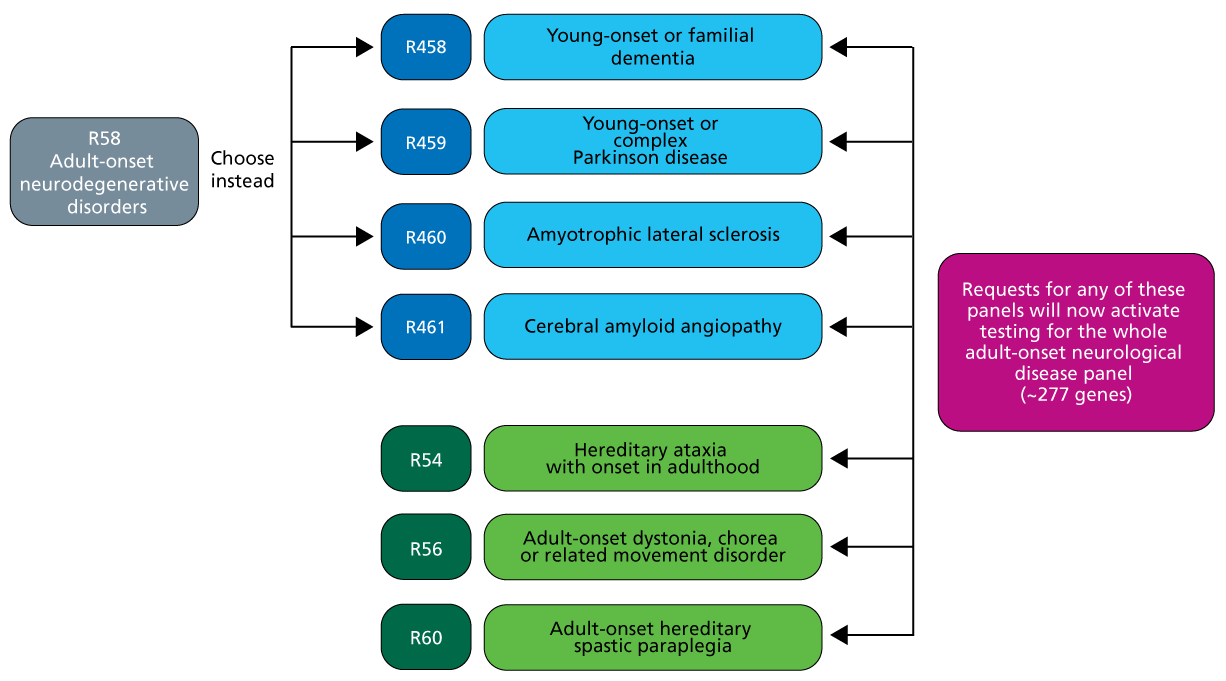
R460 Amyotrophic lateral sclerosis / Super panel
WGS considerations
- 1072 entities - 451 green
- Many non-ALS genes
- Privacy and research participation
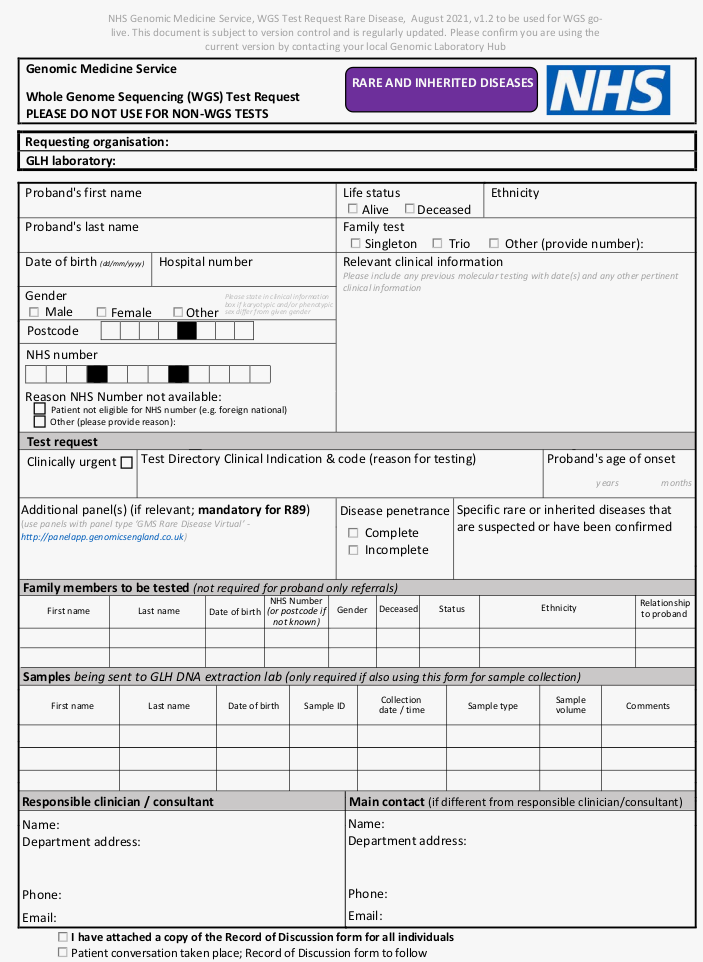
- Consent and recording
NHS genomics forms

Interpreting results
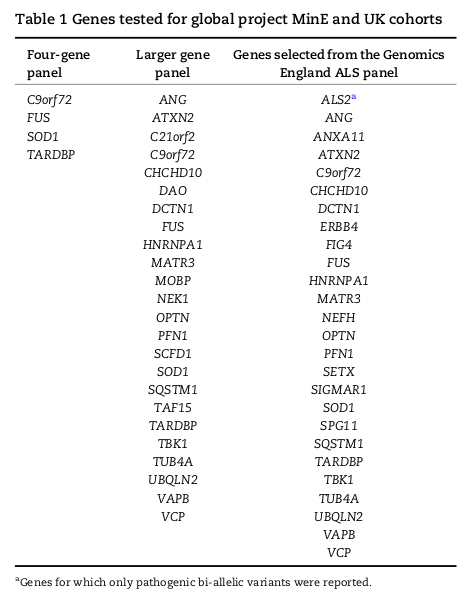
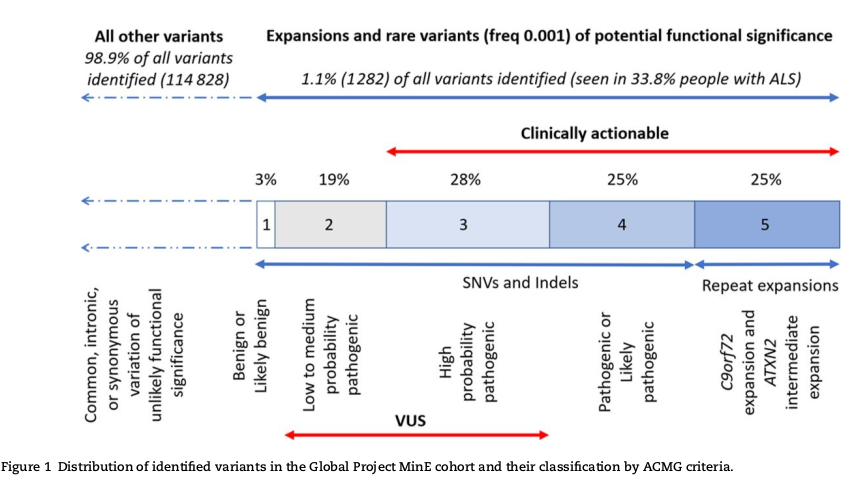
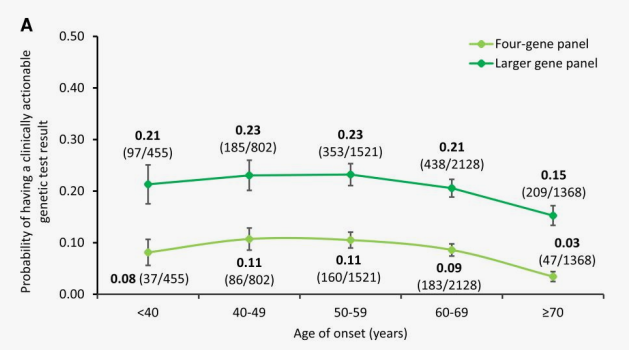
Example result

Disclosing genetic testing results
- Patients generally disclose once they have processed
- Patients can nominate relatives to have access to results after death
- Get genetics advice if patient refuses to disclose/otherwise believe at risk
- Occupational implications
- Health insurance - insurers can request Huntington's predictive test results
structure
- Scenarios
- What to do in the clinic
- Is ALS genetic?
- C9orf72
- SOD1
- FUS
C9orf72
C9orf72 hexanucleotide repeat expansion
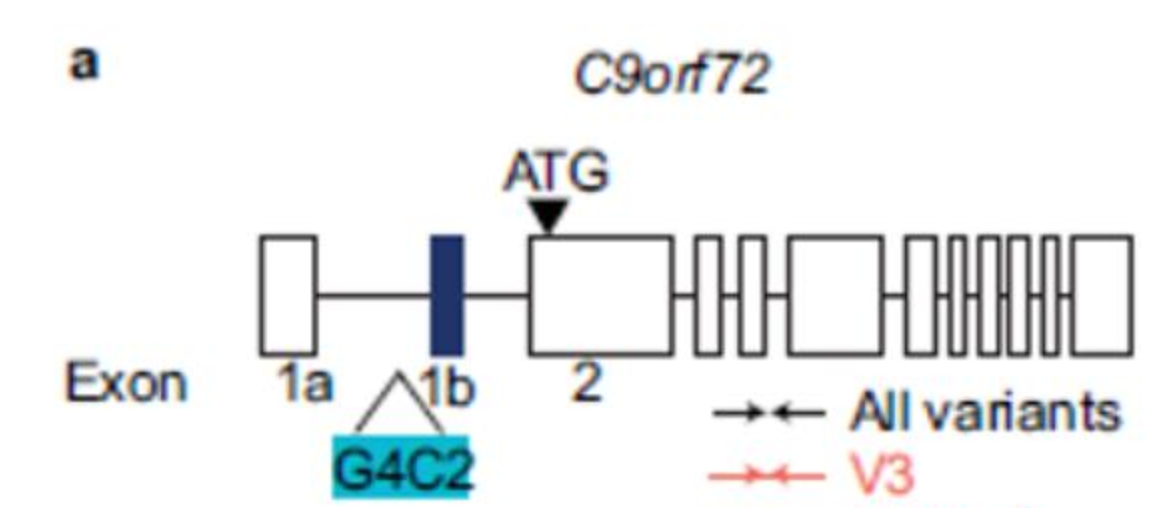
- >30 repeats, can be thousands
- Does not show anticipation
- Repeat length (in blood) does not correlate with clinical features
- Likely somatic repeat instability
Mechanism - controversial
- Loss of function - vesicle trafficking/autophagy?
- Toxic repeat RNA
- Toxic repeat proteins
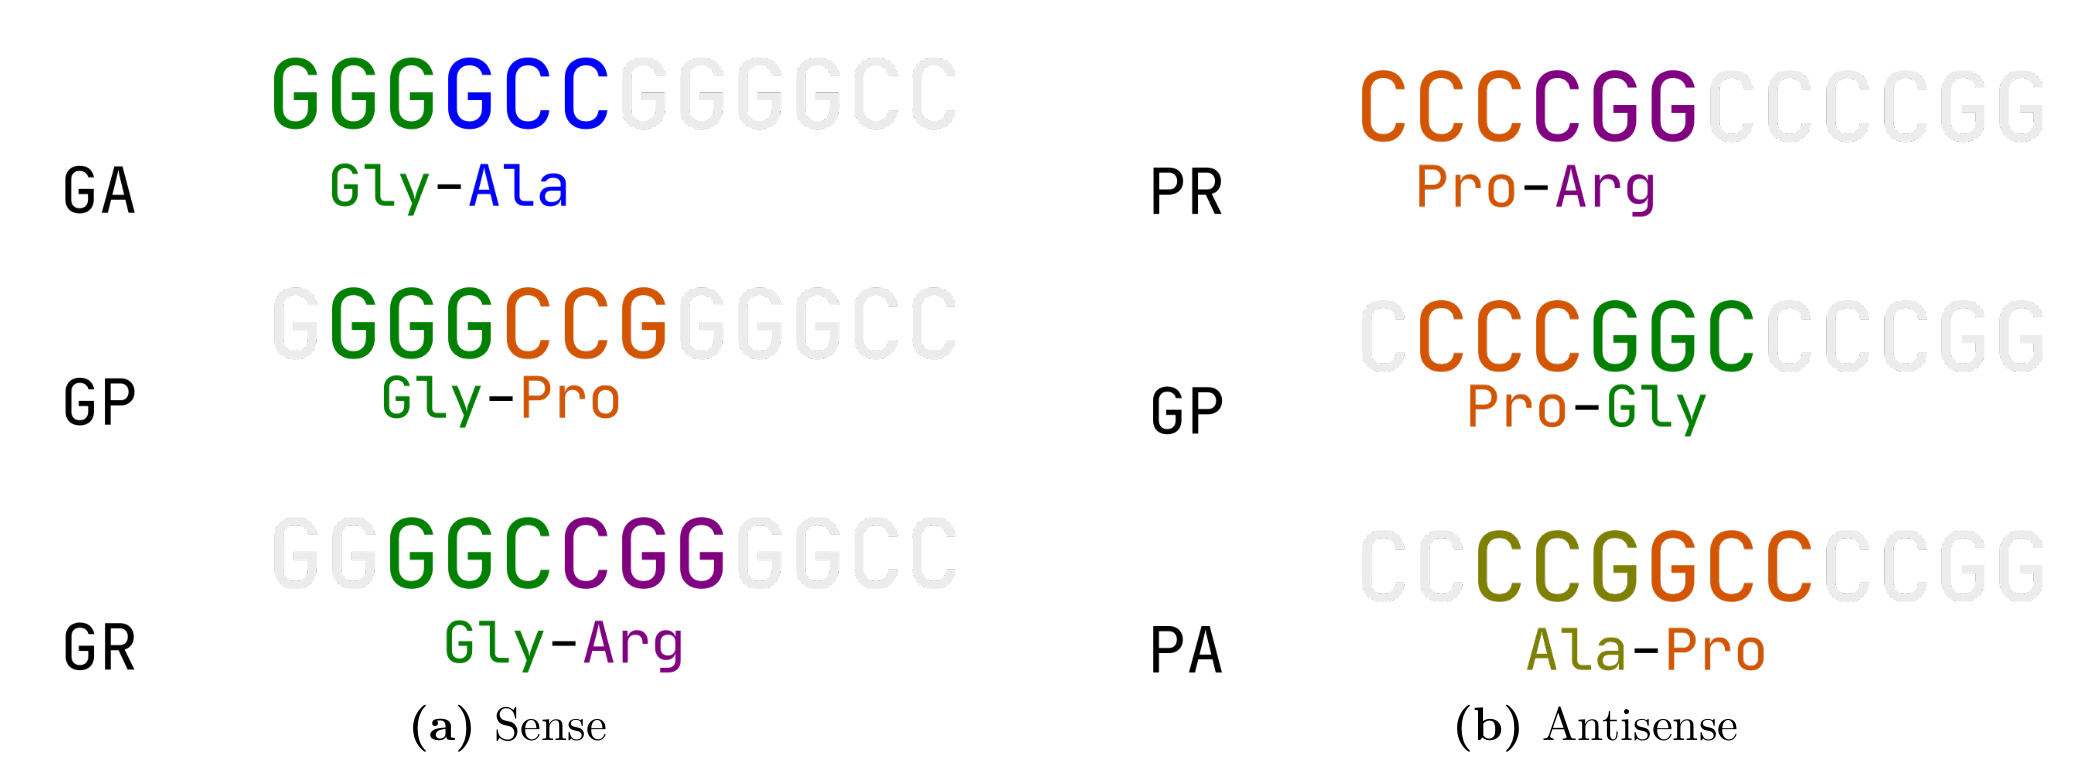
Clinical features
- Heterogeneous - ALS, FTD, or ALS+FTD
- Emerging evidence - psychosis, bipolar, not cognitively normal before symptom onset
- Family history - dementia unspecified?
Penetrance
- High (>90%) in the context of targeted testing in ALS/FTD clinics
- Healthy individuals carrying this mutation - ?0.15% Beck 2013
- Several other case reports of healthy older adults >80. Would they remain healthy?
Neuropathology
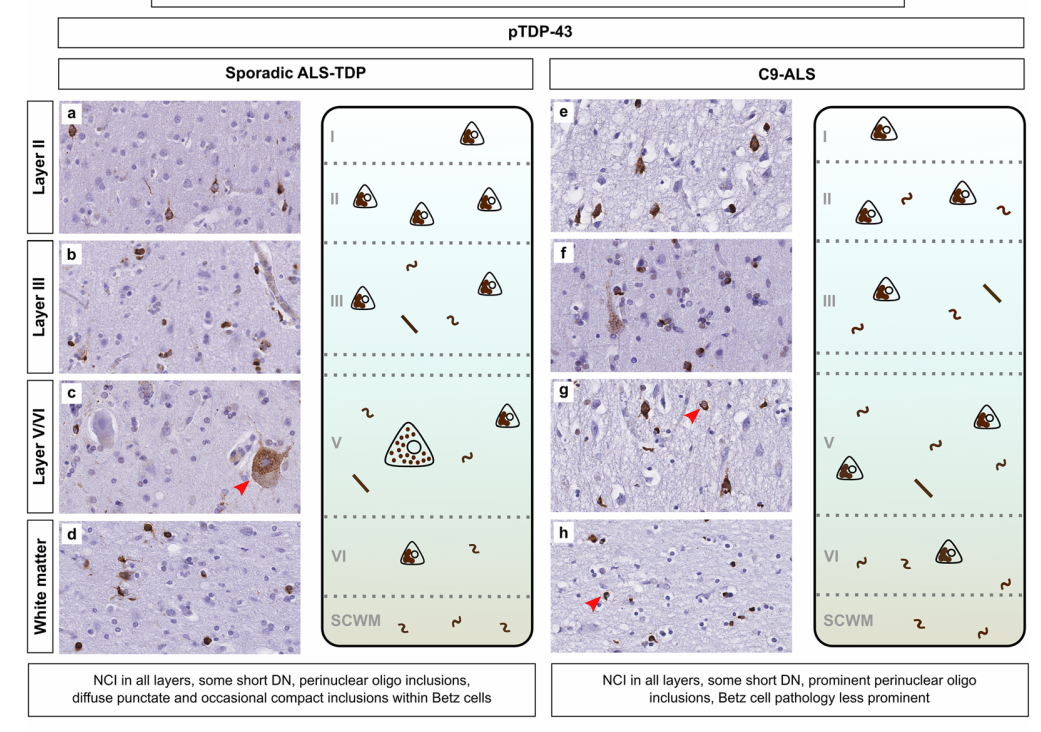
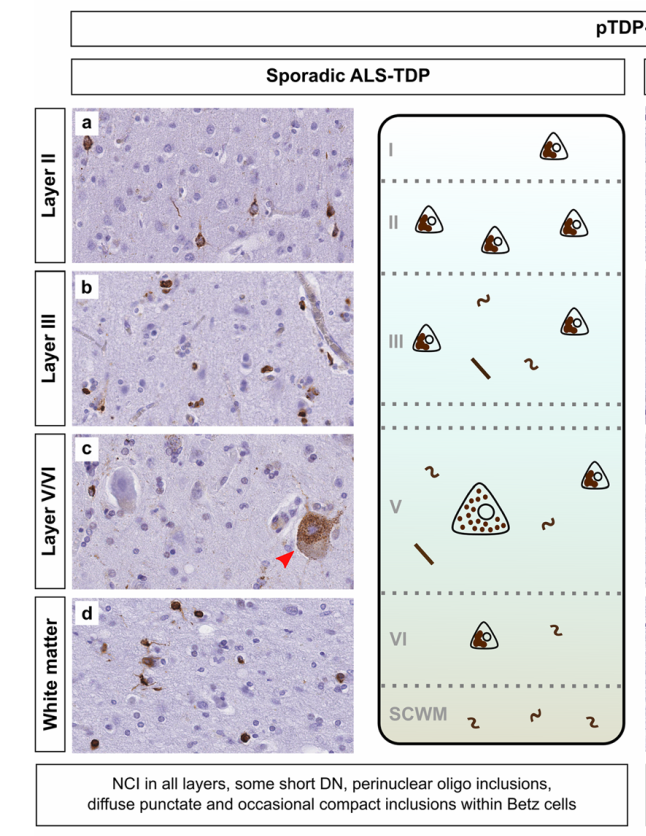
Similar (but not identical) distribution and morphology of TDP43 pathology to sporadic ALS.
Gene therapy trials in C9orf72
- Biogen trial - discontinued Mar 22
- WAVE life sciences 1b/2a trial - discontinued 2023
- Both studies showed no benefit, trial stopped by press release, companies stopped programmes
- NfL went up?
SOD1
SOD1
- Cu/Zn superoxide dismutase 1
- ~200 reported variants
- A4V - 50% in USA - aggressive course (survival 1y from diagnosis)
- heterozygous D90A - common polymorphism in Scandinavia - occasionally found in typical ALS
- homozygous D90A - slower disease course - up to 10y
- No FTD overlap
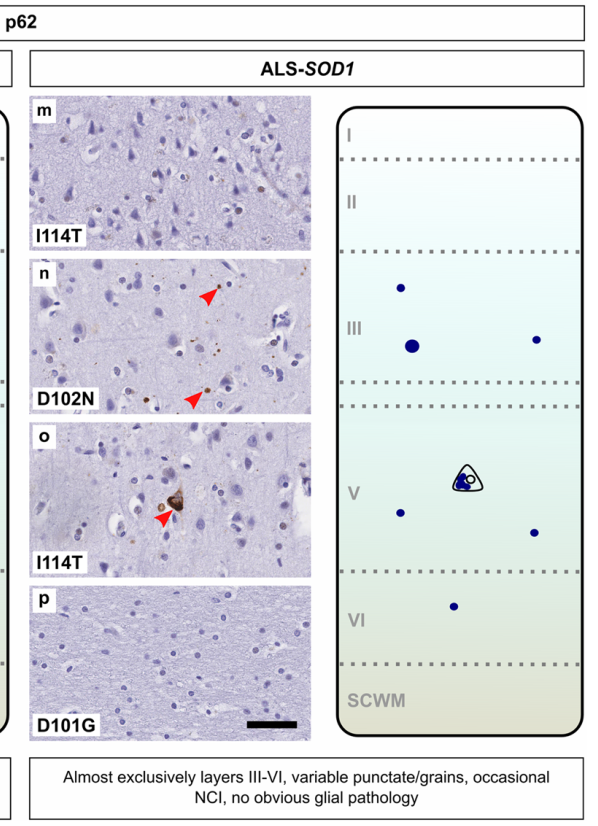
Neuropathology
- no TDP43
Tofersen - VALOR trial
- Mechanism - bind to and degrade all SOD1 RNA
- Administration - ~monthly LP
- Cost - ~400k/y?
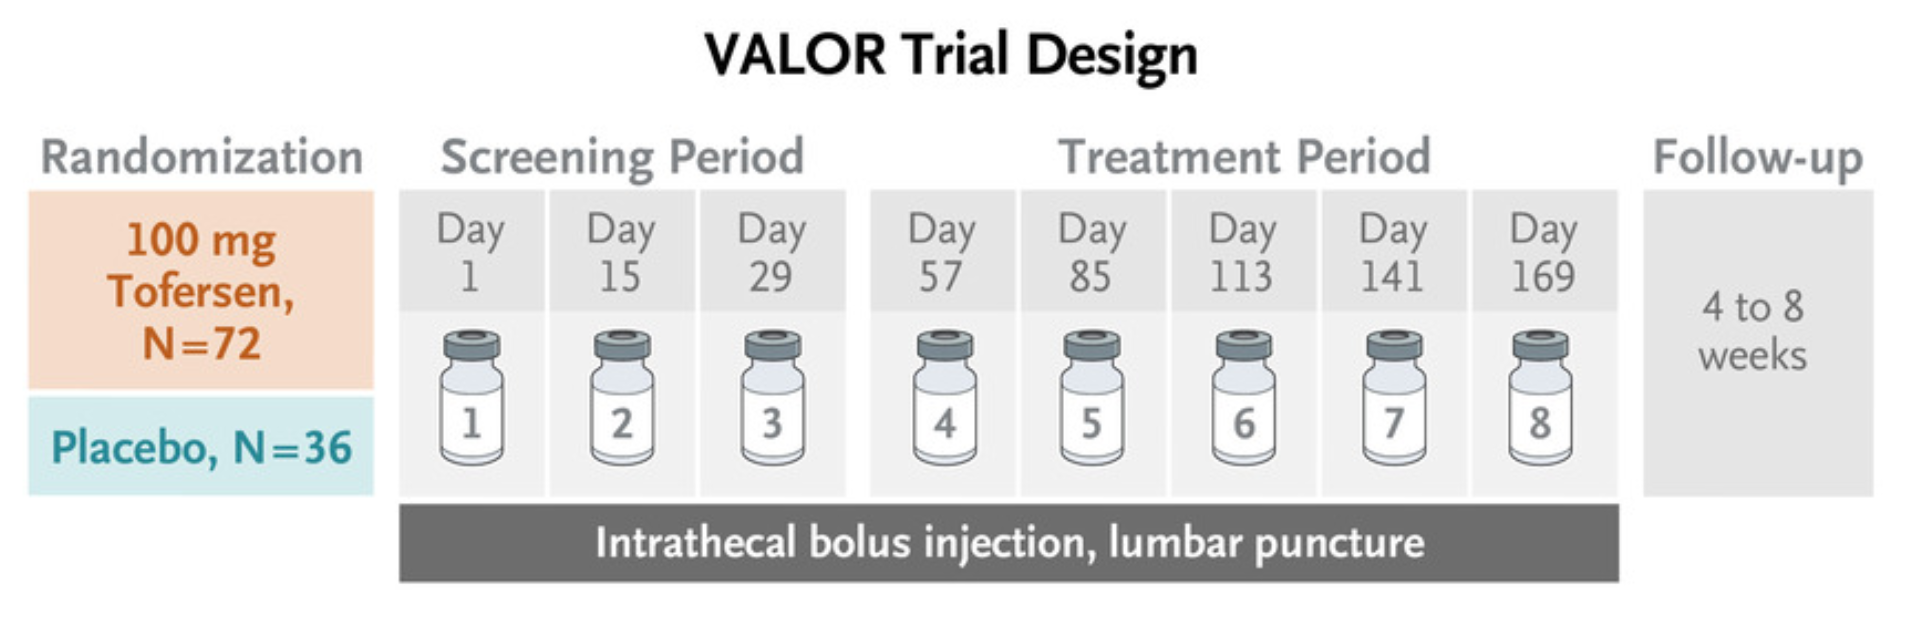
+ open-label extension
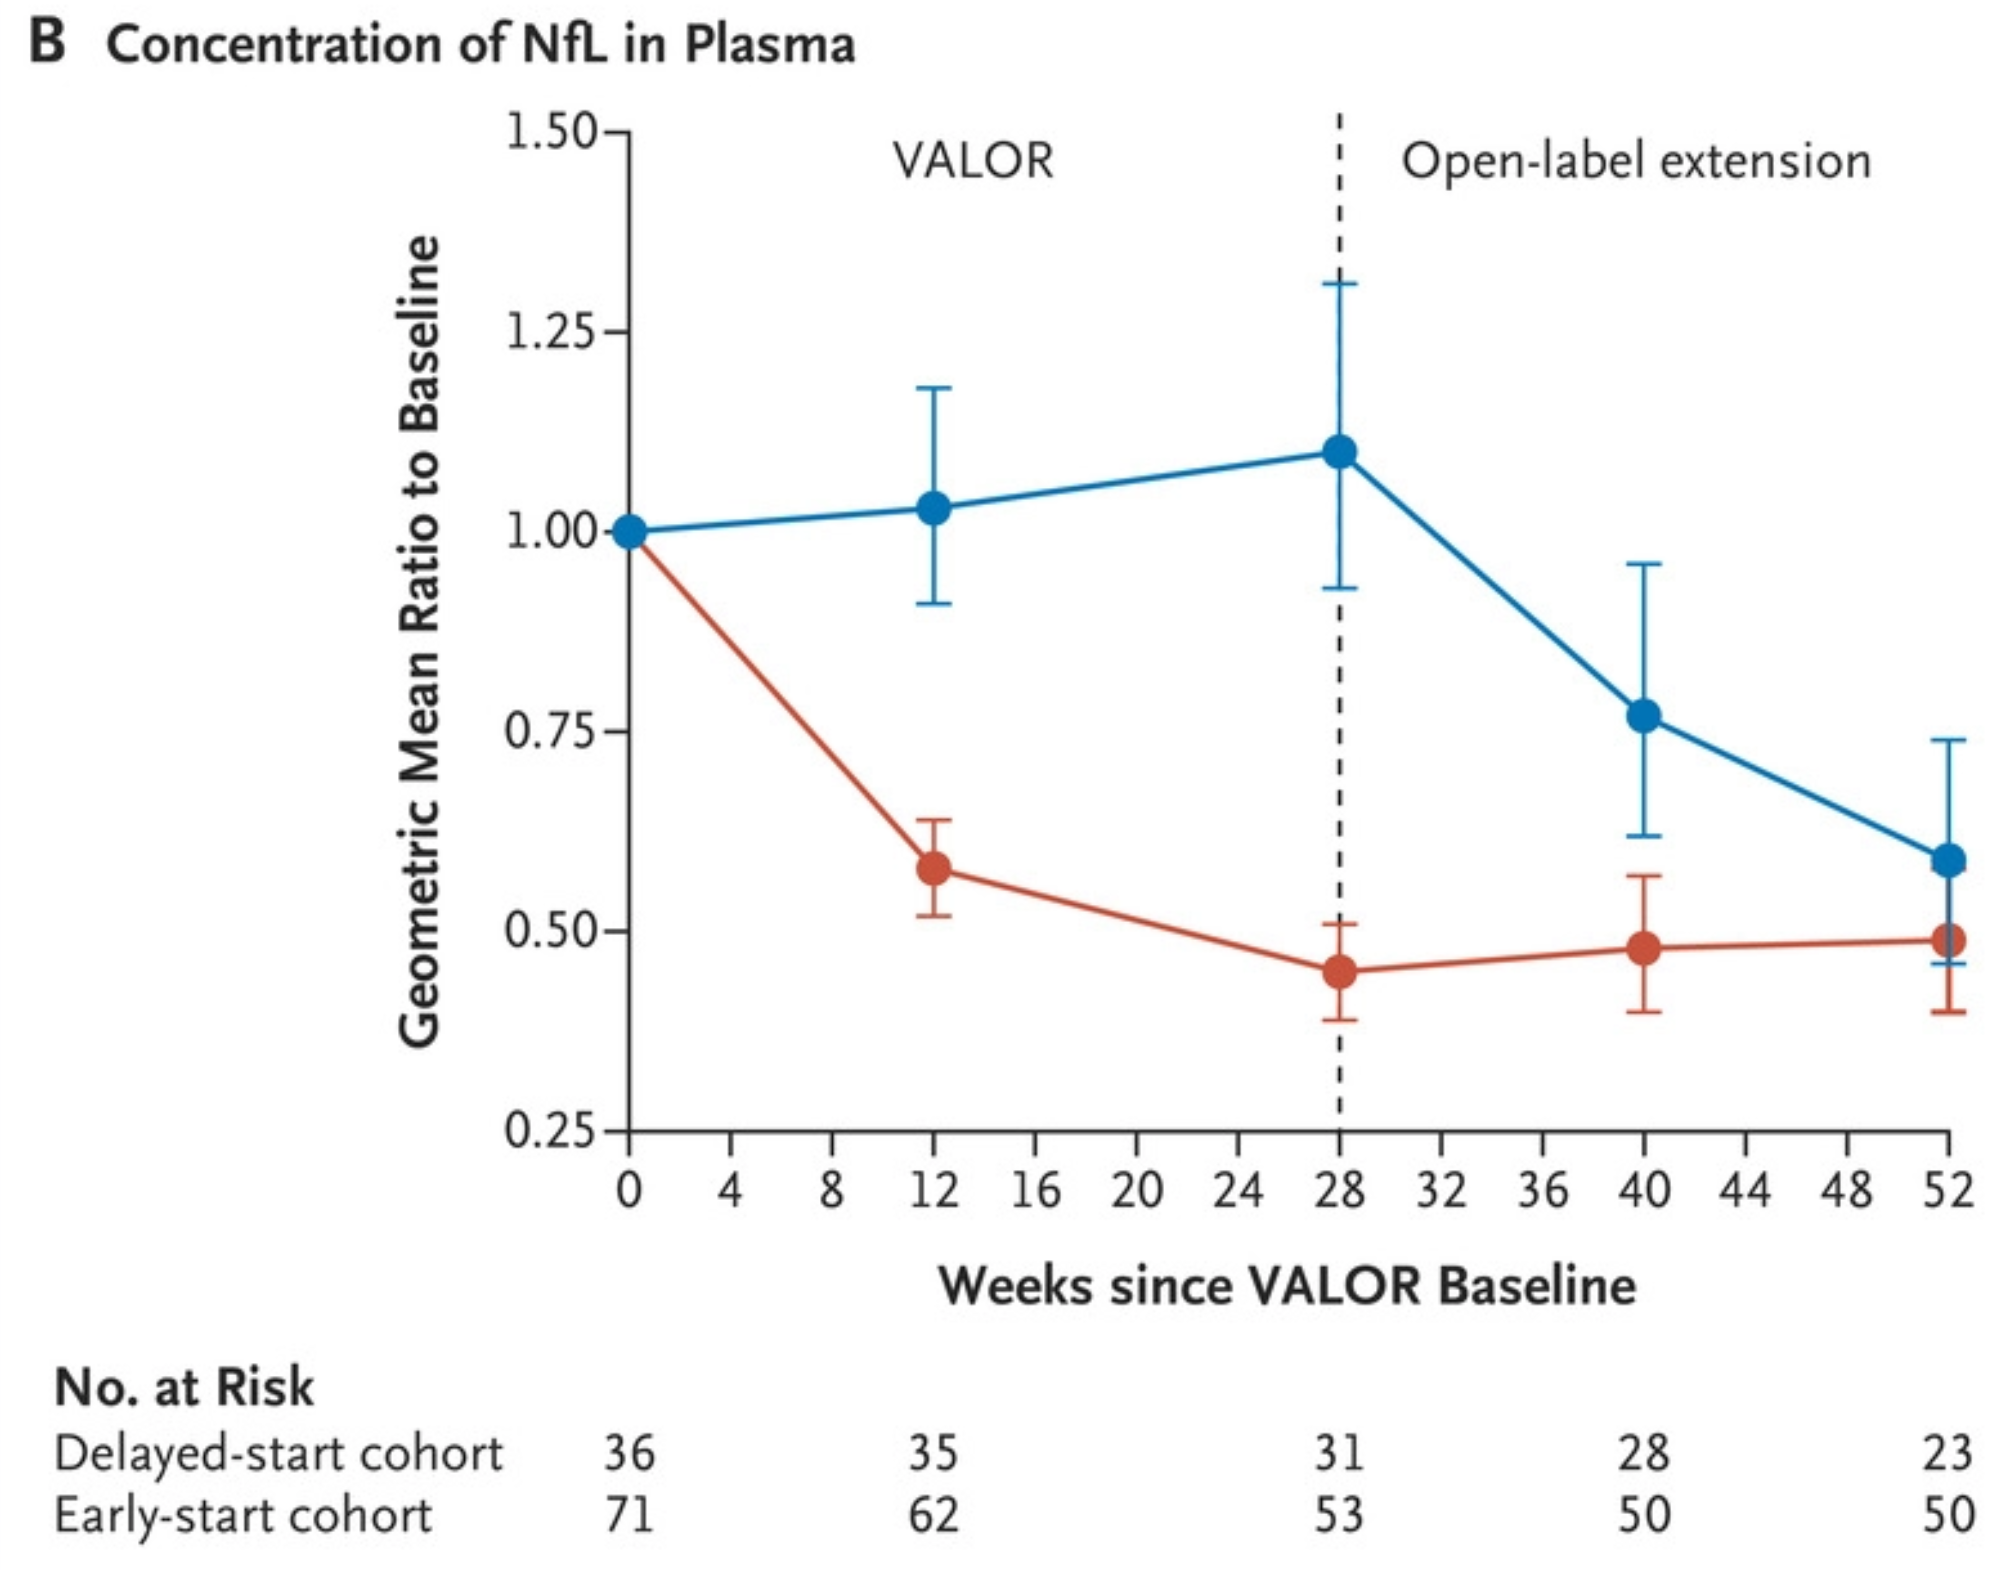
Neurofilament light
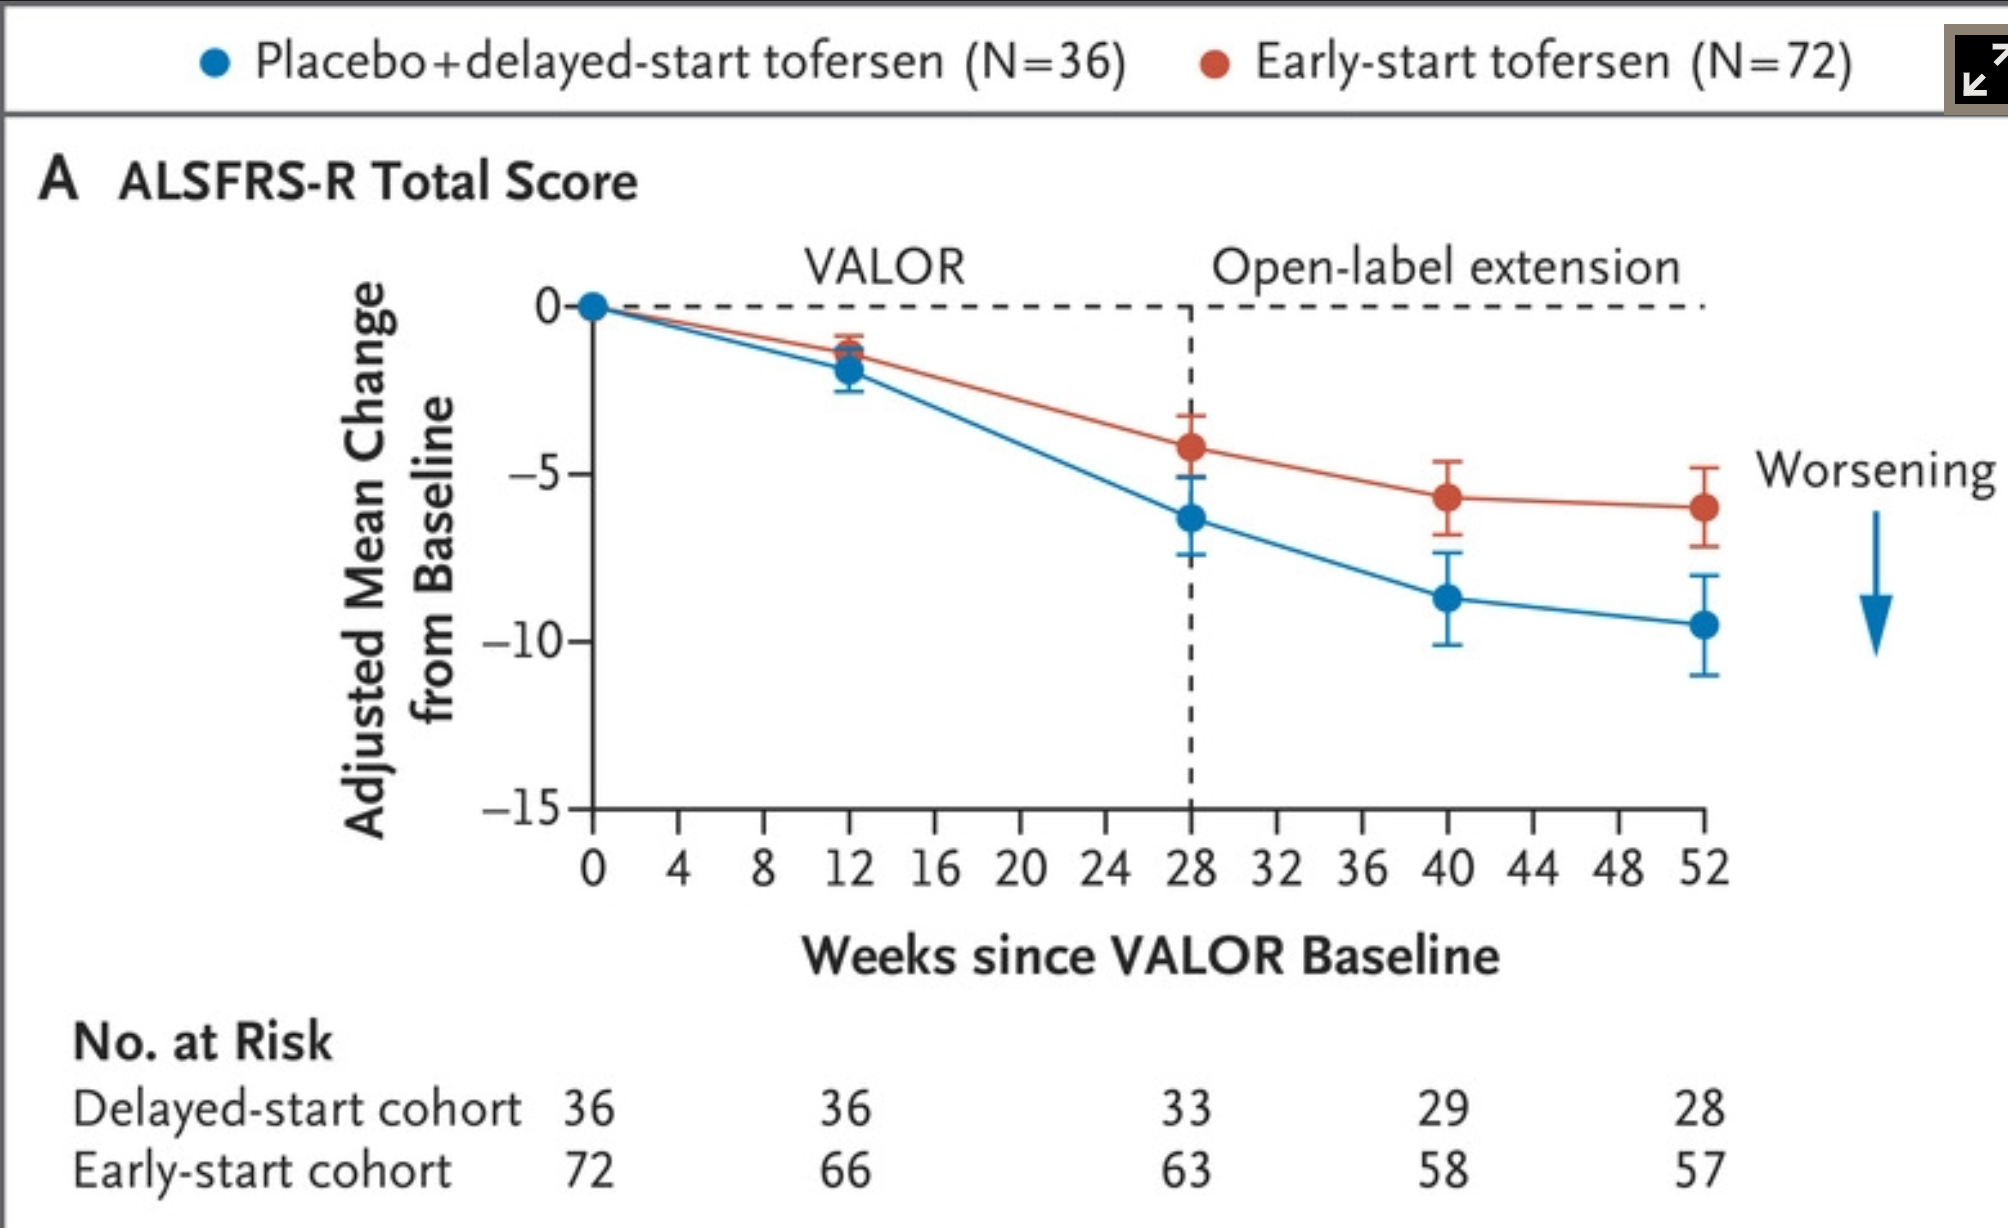
Functional rating scale
TDP43
TARDBP
- DNA binding protein
- FTD, ALS or FTD+ALS
- Why are TARDBP mutations an uncommon cause of genetic ALS?
TARDBP for modelling ALS
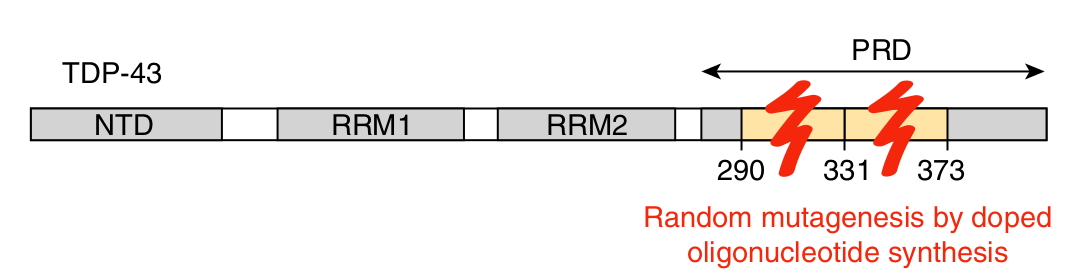
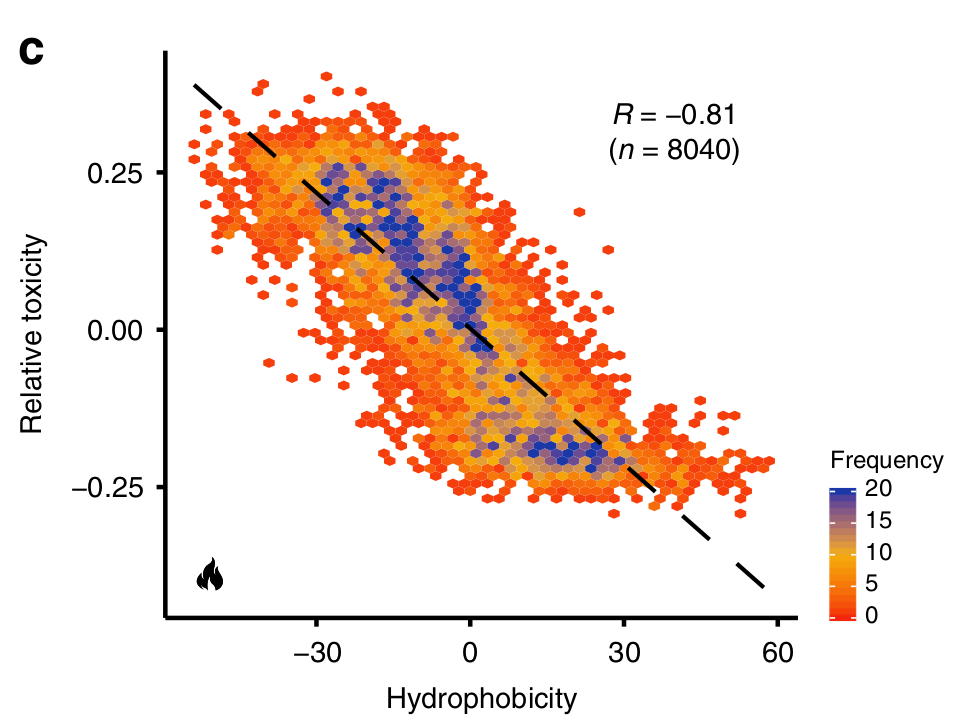
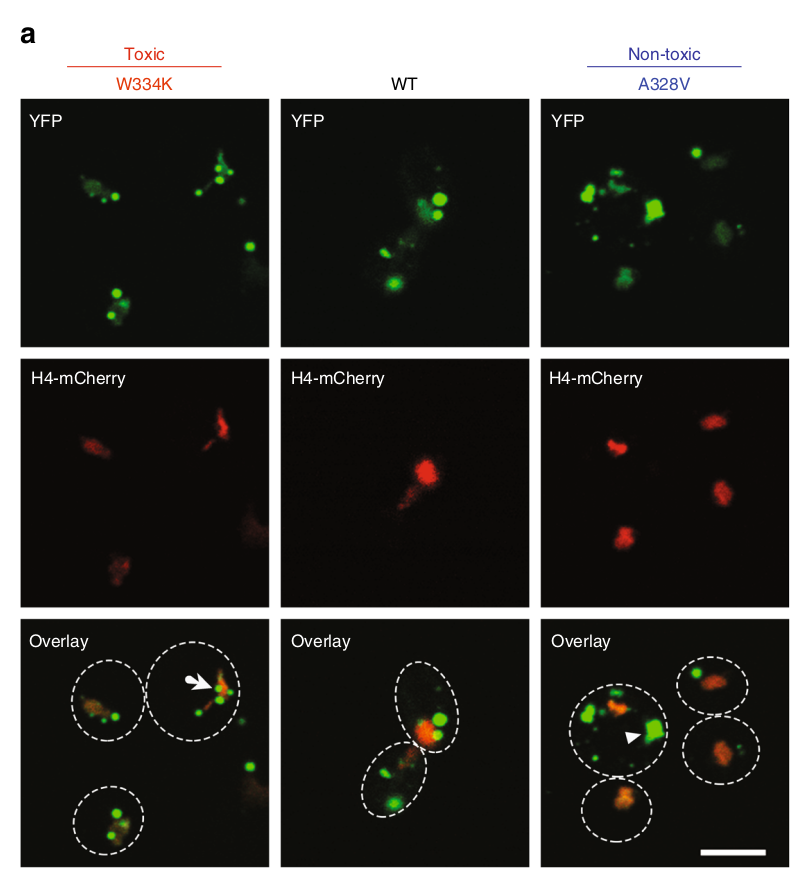
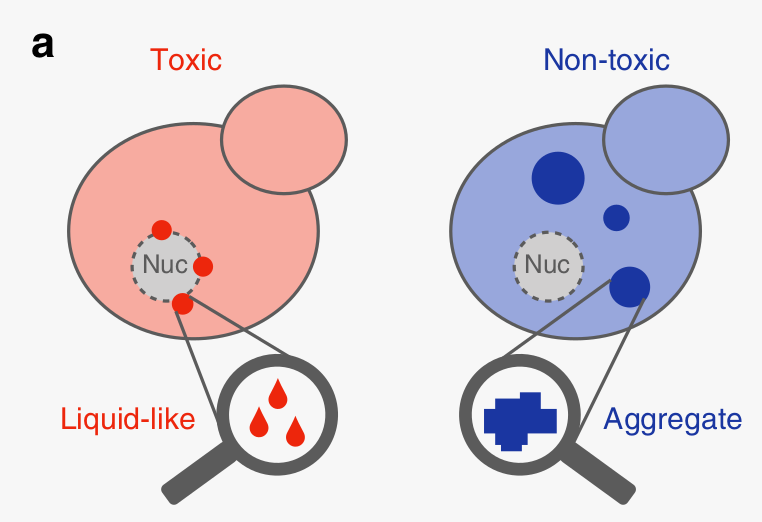
Bolognesi et. al. Nature Comm 2019 doi
FUS
FUS
- RNA binding protein
- Young onset, aggressive ALS
- essential tremor, FTD too?
- Cytoplasmic aggregates, but not TDP43
Jacifusen/Ulefnersen
- binds FUS pre-mRNA and reduce all FUS expression
- published early case series - NfL in CSF was reduced by up to 82·8% after 6 months of treatment Lancet
- FUSION trial - press release - not yet published - positive composite outcome in functional rating and survival
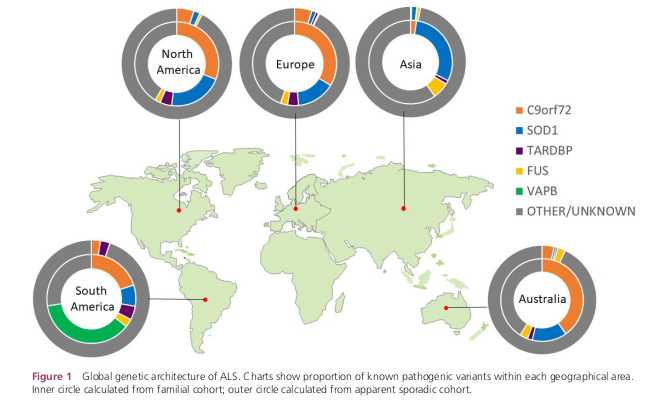
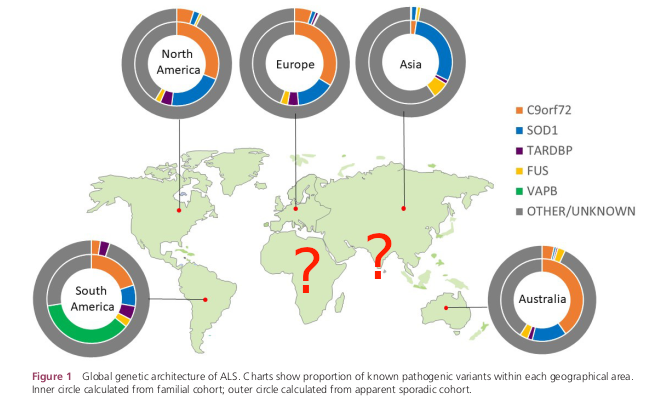
Geographic variation
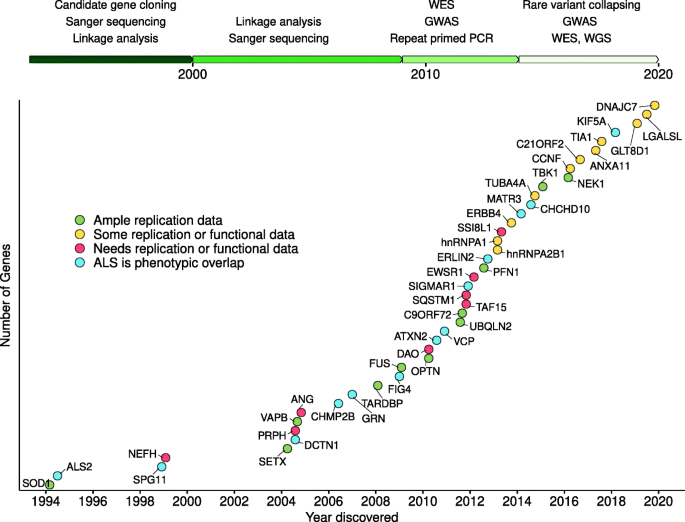
Other genes
GWAS
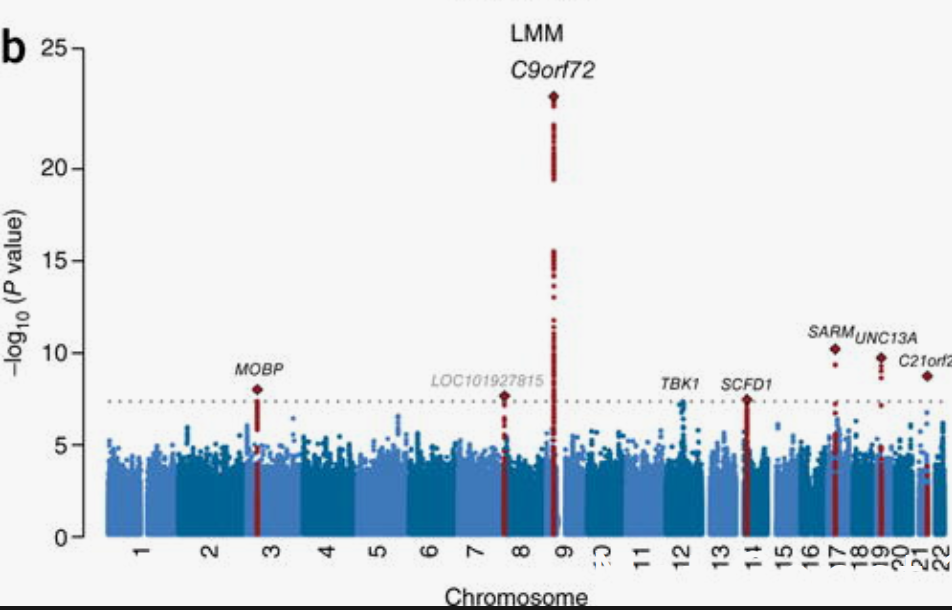
Relatively few *common* variants
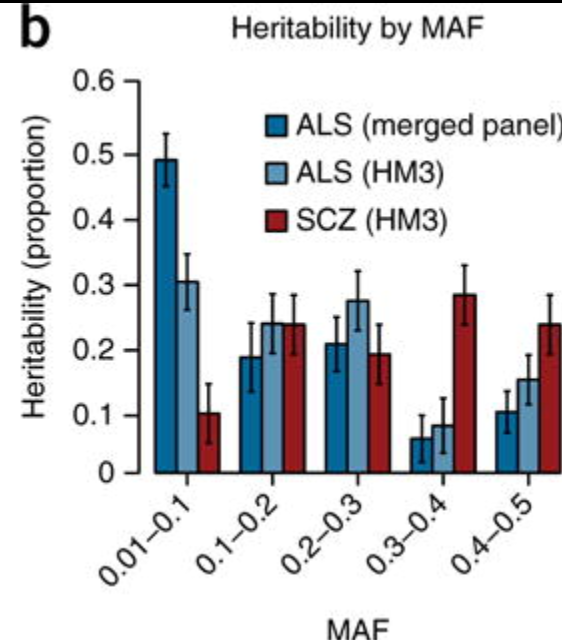
Rare variants may account for more heritability in ALS vs. schizophrenia.
Modelling ALS incidence as a multistep process
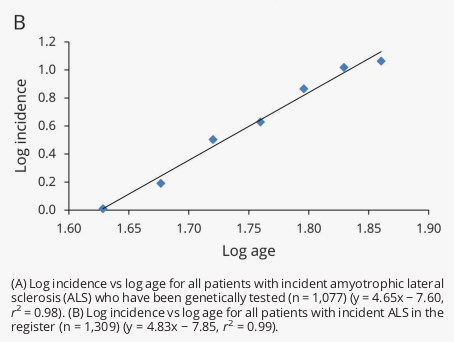
Sporadic ALS may be a 5 step process
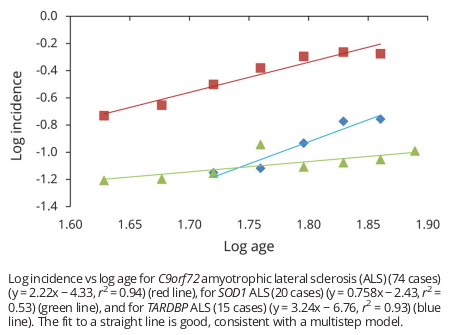
Genetic ALS may only be 2 or 3
tl;dr
- "actionable" genetics in 10-20% of ALS
- This will likely increase in proportion and complexity
- Genetics can be discussed with all ALS patients
- Testing is evolving - locally we use WGS virtual panel
- Thought/care with results
- Specialist ALS/FTD and genetics services exist